Study facts at a glance
Study population: The 48-week report describes 99 completers: 32 using 0.1% tretinoin, 35 using 0.025%, and 32 using vehicle. Source 2
Visible improvement: Both active creams improved overall facial photoaging versus vehicle; the abstract reports no clinically or statistically significant efficacy difference between concentrations. Source 2
Irritation: Redness and scaling were significantly greater with 0.1% than with 0.025% tretinoin. Source 2
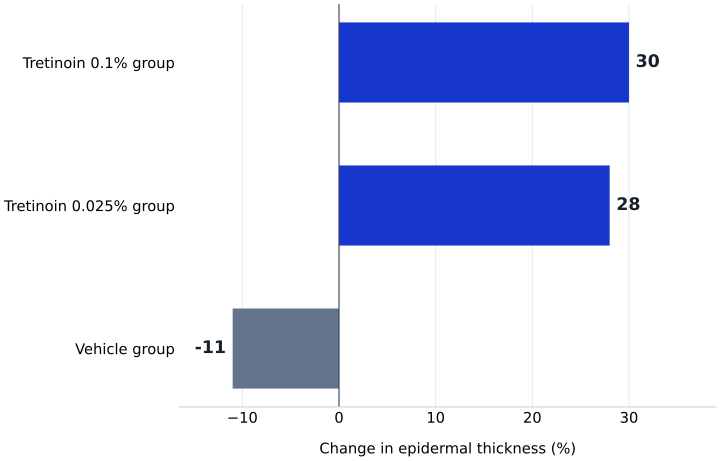
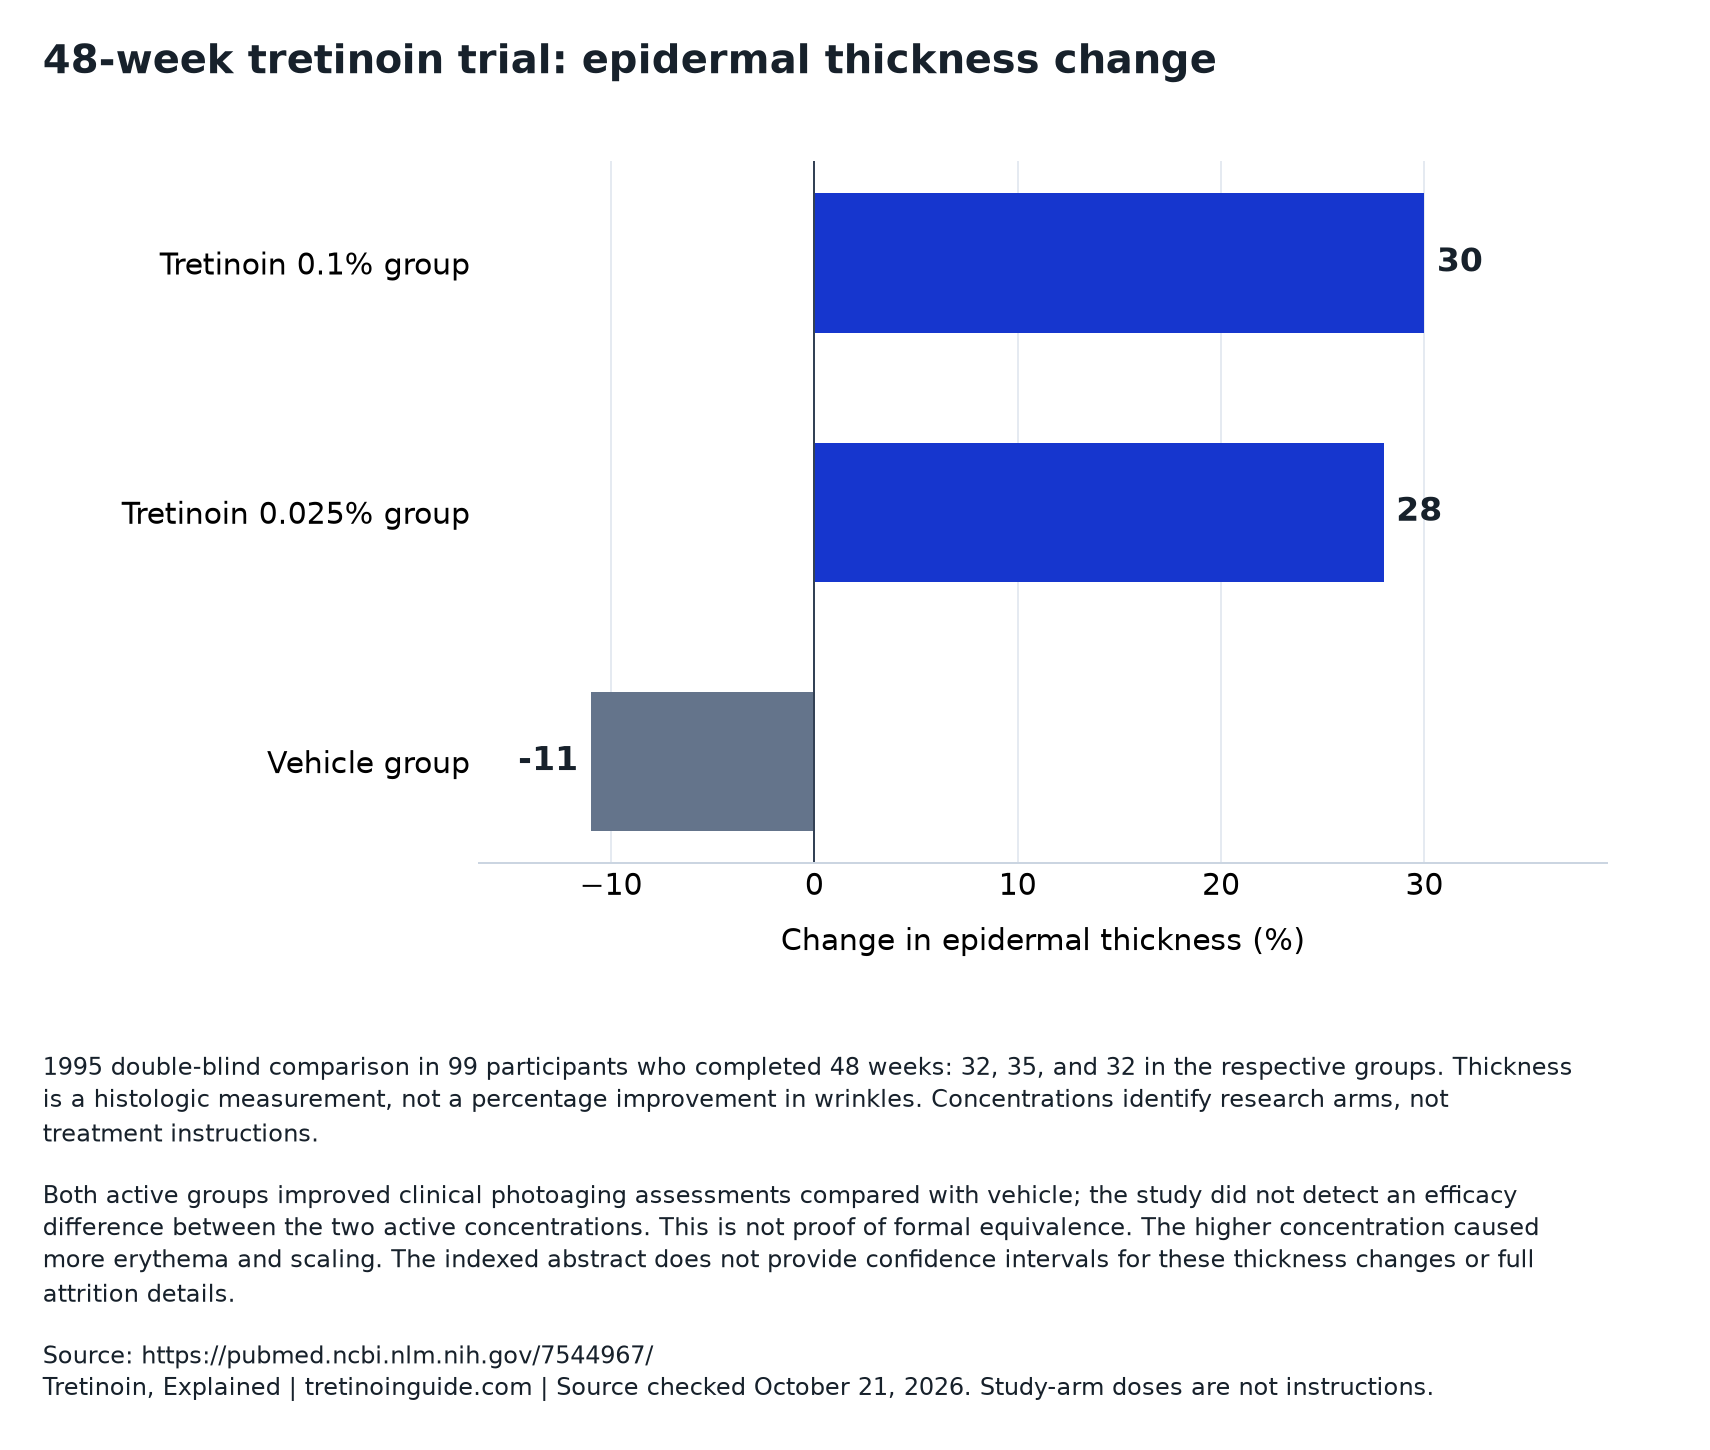
Microscopic findings: Epidermal thickness increased 30% and 28% in the active groups, versus an 11% decrease with vehicle; these are not wrinkle-reduction percentages. Source 2
Longer follow-up: A separate 204-subject trial studied 0.05% tretinoin emollient cream for up to two years, but its abstract does not provide numerical clinical effect sizes. Source 4
What the 48-week comparison actually tested
The central study involved people with photoaging: skin changes associated with chronic sunlight exposure. Participants used topical 0.1% tretinoin cream, topical 0.025% tretinoin cream, or vehicle—the cream base without tretinoin—once daily for 48 weeks. These are historical study exposures, not instructions for choosing a strength or application schedule.
The comparison was double-blind, meaning treatment identity was concealed from participants and assessors. The indexed abstract does not explicitly state random assignment, so describing this particular trial as randomized would go beyond the accessible evidence. It also does not identify a single prespecified primary endpoint or provide the clinical grading scale.
The vehicle group helps separate the contribution of the active ingredient from changes associated with the cream base and study participation. The two active groups address a narrower question: whether increasing concentration from 0.025% to 0.1% changed the observed benefit and irritation over the same follow-up period.
The three groups described among the 48-week study completers
| Study arm | Completers | Role in the comparison |
|---|---|---|
| Topical tretinoin cream 0.1% | 32 | Higher-concentration active treatment |
| Topical tretinoin cream 0.025% | 35 | Lower-concentration active treatment |
| Vehicle cream | 32 | Cream-base control without tretinoin |
Read the underlying chart data: download CSV or download the source-labeled chart.
Why 99 completers is not an enrollment count
The abstract’s wording establishes that 99 patients completed the study. It does not establish how many originally enrolled, how many began each treatment, or how many left before week 48. Consequently, neither an overall completion percentage nor a treatment-specific withdrawal rate can be calculated from these numbers.
That missing denominator matters in a study comparing irritation. If people with especially troublesome reactions were more likely to leave, their absence could affect the experience represented by the completers. This is an unresolved possibility, not evidence that such selective withdrawal actually occurred. The abstract does not supply the necessary participant flow.
The report also provides no detailed age distribution, skin-type distribution, or sponsor information in its indexed abstract. Those omissions limit judgments about representativeness and study context. They do not erase the direct concentration comparison, but they prevent a confident reconstruction of how well the final groups represented everyone who initially sought treatment.
Similar observed improvement is not proof of equivalence
Both concentrations produced statistically significant overall improvement in facial photoaging compared with vehicle. Between the two active creams, the investigators reported no clinically or statistically significant efficacy difference. This supports a practical reading: the higher concentration did not demonstrate an additional clinical advantage in this comparison.
It does not prove the concentrations are interchangeable under every circumstance. An equivalence trial needs a predefined range of differences considered acceptably small. A noninferiority trial asks whether one treatment is not worse than another beyond a specified margin. Neither framework is established in the abstract, and confidence intervals for the between-strength clinical difference are unavailable.
The distinction is important because failure to detect a difference can reflect genuinely similar effects, limited precision, or both. The abstract also does not supply the magnitude of improvement on a visible-wrinkle scale. Readers comparing claims about different treatment goals can use the acne-versus-photoaging guide to keep the clinical question explicit.
Skin thickness percentages are not wrinkle percentages
After 48 weeks, epidermal thickness increased by 30% with 0.1% tretinoin and 28% with 0.025%, while the vehicle group showed an 11% decrease. The epidermis is the outer cellular layer of skin. These measurements describe tissue structure under microscopic examination, not the proportion of participants who looked better or the percentage of fine lines that disappeared.
A worked interpretation helps: if a thickness measurement started at an illustrative 100 units, a 30% increase would bring it to 130 units. That arithmetic says nothing about a wrinkle score unless a separate analysis connects the two. The difference between the active groups’ reported changes was 2 percentage points, not proof of a 2% cosmetic advantage.
Vascularity, measured through dermal endothelial cell area, rose 100% and 89% in the active groups and fell 9% with vehicle. Endothelial cells line blood vessels; a 100% increase means the measured area doubled relative to baseline. It does not mean circulation became twice as healthy, or that appearance improved twice as much. Absolute baseline measurements and confidence intervals are not supplied.
Irritation and improvement did not move together
Redness, termed erythema, and scaling were statistically significantly greater with 0.1% tretinoin than with 0.025% across the reported analyses. Yet the higher-strength group did not show a corresponding clinical advantage. This separation is the study’s most informative contribution to the common belief that peeling is evidence of a stronger result.
The authors interpreted the pattern as suggesting that mechanisms other than irritation dominate tretinoin-associated changes in photoaged skin. That is a mechanistic inference from the comparison, not a direct experiment switching irritation on and off. It does not establish that irritation plays no role, or that every individual can improve without experiencing it.
The abstract supplies no irritation percentages, severity distribution, or time course, so the size of the tolerability difference cannot be quantified here. Questions about how symptoms are documented and reviewed are more useful than treating discomfort as a success marker; the first-month follow-up guide organizes that discussion without turning this trial into a personal regimen.
The immune measurements answered a limited question
The investigators also examined skin immune-system features before and after treatment. These included keratinocyte expression of HLA-DR and intercellular adhesion molecule-1, epidermal Langerhans cells, and epidermal and dermal T lymphocytes. In plain language, they assessed selected cell populations and signals involved in immune recognition and communication.
No significant changes in these immunologic markers were reported when tretinoin and vehicle treatments were compared. This is a distinct result from the increases in thickness and vascularity. It shows why a study should not be summarized as though every biological measurement shifted in the same direction.
Unchanged selected markers do not establish unchanged immune function in every respect. The abstract gives neither numerical estimates nor confidence intervals for these comparisons, and it reports no clinical infection or cancer-prevention endpoint. The useful conclusion is specific: the measured immune markers did not show a statistically significant treatment difference over the study interval.
What the two-year tretinoin study adds
A separate 2005 randomized, placebo-controlled trial studied topical 0.05% tretinoin emollient cream in 204 subjects with moderate to severe facial photodamage. Treatment or vehicle was applied to the entire face once daily for up to two years, with clinical and microscopic assessments at scheduled visits. Unlike the concentration comparison, this study is explicitly described as randomized.
Tretinoin produced significantly greater improvement than vehicle in fine and coarse wrinkling, mottled hyperpigmentation, lentigines, sallowness, overall photodamage severity, and investigator global response. The abstract gives significance thresholds but not clinical score changes, response percentages, or confidence intervals. It therefore supports longer-duration efficacy without allowing a numerical comparison against the 1995 strengths.
Histologic assessment found no increase versus vehicle in keratinocytic or melanocytic atypia, dermal elastosis, or adverse stratum-corneum changes. Atypia means abnormal-looking cells; the stratum corneum is the outermost skin layer. These are reassuring findings for the measured tissue features, not a complete adverse-event account or evidence of cancer prevention.
At month 12, a three-center immunohistochemistry analysis found increased procollagen 1C terminal, a marker of procollagen synthesis. This is a biological signal rather than a direct measurement of visible wrinkle benefit or durable collagen function. The abstract does not give its effect size, detailed local-reaction rates, or sponsor information.
Retinol in adults averaging 87 is a separate experiment
The 2007 retinol study involved 36 residents of two senior facilities, with a mean age of 87. It was a randomized, double-blind, vehicle-controlled comparison between the arms of each participant. Study personnel applied 0.4% retinol lotion or vehicle up to three times weekly for 24 weeks. The ingredient, skin site, population, and duration all differed from the facial tretinoin studies.
Fine-wrinkling scores on a 0–9 severity scale changed by −1.64 with retinol, with a 95% confidence interval of −2.06 to −1.22, versus −0.08 with vehicle, with an interval of −0.17 to 0.01. The difference between the reported mean changes is 1.56 scale points favoring retinol, not a percentage reduction. The analysis used last observation carried forward for missing follow-up measurements.
Biopsy subgroups were small: six participants for glycosaminoglycan expression and four for procollagen I staining. Those findings do not establish fewer injuries or ulcers. The closer reading of the retinol study in adults averaging 87 develops these distinctions; the ingredient and compounding guide explains why percentage strengths across different ingredients are not a potency ranking.
Three experiments that answer different questions
| Evidence | Population and exposure | Main interpretive boundary |
|---|---|---|
| 1995 concentration comparison | 99 completers with photoaging; 0.1% or 0.025% topical tretinoin cream versus vehicle; 48 weeks | Similar observed efficacy does not establish formal equivalence |
| 2005 longer-term trial | 204 subjects with moderate to severe facial photodamage; 0.05% topical tretinoin emollient cream versus vehicle; up to two years | Abstract reports improvement but no numerical clinical effect sizes |
| 2007 retinol trial | 36 adults averaging 87; 0.4% topical retinol lotion versus vehicle on opposite arms; 24 weeks | Not a facial tretinoin trial or a head-to-head ingredient comparison |
RENOVA’s label is narrower than an anti-aging promise
The official labeling concerns RENOVA tretinoin cream 0.02%, an exact formulation distinct from the creams in the 48-week comparison. Its indication is mitigation of fine facial wrinkles as an adjunct to comprehensive skin care and sunlight avoidance. It does not establish wrinkle elimination, reversal of photoaging, or restoration of younger skin.
The label describes five controlled studies lasting 24 weeks, with 324 evaluable RENOVA recipients and 332 vehicle recipients. Two studies adequately demonstrated efficacy for fine facial wrinkling. The broader endpoints—including coarse wrinkles, roughness, pigmentation changes, and laxity—did not meet that replicated-efficacy standard. A single-center study in darker-pigmented participants did not demonstrate benefit over vehicle plus the skin-care program.
Safety findings are concrete: almost all treated patients reported local reactions in the label’s adverse-reaction account. A category covering severe irritation, temporary interruption, or mild topical corticosteroid use occurred in 32%; about 4% discontinued because of adverse reactions. These figures are not rates from the 1995 comparison. The label also addresses pregnancy, photosensitizing medicines, and sunburn susceptibility.
The label states that safety and efficacy of daily RENOVA 0.02% beyond 52 weeks have not been established. The separate two-year 0.05% trial does not automatically remove that formulation-specific limitation. The prescription-label guide helps separate concentration, cream base, indication, and warnings. Bausch Health US LLC is the listed packager; that does not identify sponsorship of the historical studies.
What this evidence changes about a prescription discussion
The strongest question emerging from the 48-week study is not simply which percentage is highest. It is what outcome a particular product is intended to improve, what evidence supports that formulation, and how adverse effects will be assessed. A microscopic change, a clinician-rated photoaging score, and a person’s satisfaction with fine lines are related possibilities, not interchangeable endpoints.
Editorial interpretation: a higher advertised strength should not by itself be treated as evidence of better value. The study did not measure prices, subscriptions, access, or provider performance. Its results also do not transfer automatically to compounded blends, gels, lotions, oral products, or a provider’s care model. Those require their own documentary and clinical evaluation.
For readers evaluating service terms, the Curology review and Dermatica review can be used to check product descriptions, renewal language, and other documents—not as evidence that either service reproduces these trials. The scientific takeaway remains narrower: over 48 weeks, a fourfold concentration difference produced more irritation without demonstrating more clinical improvement.
Questions about the evidence
Did 0.025% tretinoin work as well as 0.1%?
The 48-week abstract reports similar observed clinical improvement and no clinically or statistically significant efficacy difference. That supports saying the higher concentration did not demonstrate extra benefit in this study. It does not support formal equivalence, because an equivalence margin and confidence interval for the difference are not available.
Does a 30% increase in epidermal thickness mean 30% fewer wrinkles?
No. Epidermal thickness is a tissue measurement, while wrinkle severity is a clinical appearance outcome. The study reported both types of assessment but did not provide a conversion between them. A percentage increase in thickness cannot be relabeled as a percentage cosmetic improvement.
Is peeling necessary for tretinoin to work?
The study argues against using greater peeling as a marker of greater benefit: the higher concentration caused more scaling and redness without greater observed efficacy. It does not prove that irritation is absent from every successful treatment course or establish exactly which biological mechanisms account for improvement.
Does the two-year trial establish indefinite safety?
No. It extends observation for one 0.05% emollient formulation and reports reassuring findings for specified microscopic outcomes. Its abstract does not provide a complete adverse-event breakdown. RENOVA 0.02% has separate labeling, including its own duration limitation, and neither report establishes lifetime safety.
Can the retinol arm study identify the best facial tretinoin strength?
No. It tested a different ingredient on arm skin in adults averaging 87, using a within-person vehicle comparison over 24 weeks. It provides evidence about that retinol intervention, not a head-to-head comparison with tretinoin or a basis for choosing among facial tretinoin concentrations.
What this evidence supports
The 48-week comparison supports a specific, useful conclusion: 0.1% tretinoin caused more irritation than 0.025% without demonstrating additional clinical improvement among the reported completers. Its structural skin findings strengthen the evidence that biological changes occurred, but they are not wrinkle-reduction percentages. Longer-term tretinoin and separate retinol research add context without resolving the optimal concentration, the importance of missing participants, or how closely tissue changes predict visible results. A sound prescription discussion keeps those questions separate from product strength alone.
Research access and limitations
Research analysis is based on indexed primary-report abstracts, alongside the full official RENOVA labeling. Full study protocols, participant-flow details, clinical effect-size confidence intervals for the tretinoin comparisons, and research sponsorship details were not available in those abstracts. Historical trial exposures are described for interpretation, not as individualized treatment instructions.